Understanding PCOS and PCOD: What’s the Real Difference
PCOS (Polycystic Ovary Syndrome) and PCOD (Polycystic Ovary Disease) are two of the most commonly confused terms in women’s health. They get used interchangeably in everyday conversation, in casual online searches, and sometimes even in informal clinical discussion, but they are not the same condition. Understanding the distinction matters because it directly affects how a woman is diagnosed, what she’s told about her long-term health risks, and what treatment approach actually helps her.
What PCOD Actually Is
PCOD, or Polycystic Ovary Disease, refers to a condition where the ovaries produce a large number of immature or partially mature eggs, which eventually turn into small cysts within the ovaries. It is considered a far more common condition than PCOS, and in most cases, it’s linked closely to lifestyle patterns and everyday hormonal fluctuations rather than a deep-rooted metabolic disorder.
Some important characteristics of PCOD:
✅ It affects a large proportion of women of reproductive age, and many cases go undiagnosed for years because symptoms are mild.
✅ The ovaries in PCOD are often enlarged and contain multiple small cysts, but the condition doesn’t necessarily involve severe hormonal imbalance.
✅ Women with PCOD can often still ovulate, just irregularly, meaning fertility is affected less severely than in PCOS.
✅ It is frequently linked to factors like poor diet, sedentary lifestyle, chronic stress, and disrupted sleep patterns.
✅ With consistent lifestyle changes such as weight management, regular exercise, and dietary adjustments, PCOD often improves significantly, sometimes without long-term medication.
In many clinical settings, PCOD is treated as the milder end of a spectrum, something that responds well when caught early and managed proactively, rather than a condition that necessarily escalates into a serious, chronic metabolic disorder.
What PCOS Actually Is
PCOS, or Polycystic Ovary Syndrome, is a more complex endocrine and metabolic disorder. Rather than being a straightforward reproductive issue, it involves a broader disruption across the body’s hormonal systems, particularly involving androgens (male hormones present in smaller quantities in women) and insulin regulation.
Key features of PCOS:
✅ The ovaries produce excess androgens, which can lead to symptoms like excess facial or body hair growth, acne, and scalp hair thinning.
✅ Many women with PCOS also have some degree of insulin resistance, meaning their body doesn’t respond to insulin as efficiently, which raises the risk of developing type 2 diabetes over time.
✅ Ovulation is frequently irregular or absent altogether, making PCOS one of the leading causes of infertility in women of reproductive age.
✅ PCOS is associated with a higher long-term risk of cardiovascular disease, high cholesterol, high blood pressure, and metabolic syndrome.
✅ It’s a lifelong condition in most cases, meaning it’s managed rather than “cured,” though symptoms can be significantly controlled.
Unlike PCOD, PCOS is classified as a syndrome, meaning it presents as a cluster of symptoms and metabolic changes that don’t have a single identifiable cause, but rather a combination of genetic predisposition, hormonal imbalance, and lifestyle-related triggers working together.
Why the Two Get Confused So Often
The overlap in symptoms between PCOD and PCOS is the primary reason for the widespread confusion. Both conditions can involve:
✅ Irregular or missed menstrual periods
✅ Weight gain, particularly around the abdomen
✅ Acne and oily skin
✅ Mood fluctuations and, in some cases, symptoms of anxiety or low mood
✅ Difficulty conceiving
Because these symptoms look similar on the surface, many women self-diagnose based on internet searches or assume that because someone they know has “PCOS,” their own symptoms must indicate the same thing. In reality, distinguishing between the two requires actual clinical evaluation rather than symptom matching.
The Diagnostic Process: How Doctors Actually Tell Them Apart
A proper diagnosis typically combines several elements, not just a single test or scan:
Clinical history and physical examination. The doctor will ask about menstrual cycle patterns, weight changes, hair growth patterns, skin changes, and family history of diabetes, thyroid disorders, or PCOS itself, since there is a genetic component to susceptibility.
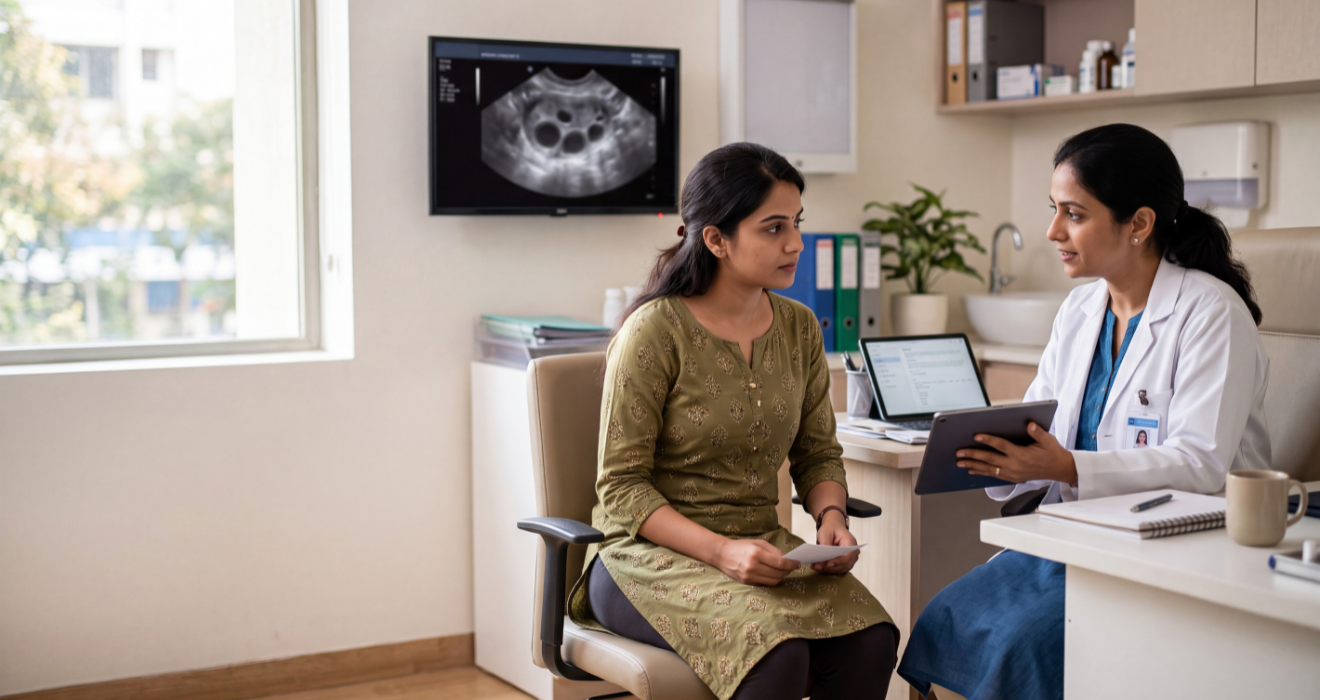
Pelvic ultrasound. This helps visualize the ovaries directly, checking for the number and size of follicles present, ovarian volume, and overall ovarian structure. While the name suggests “cysts,” what’s usually seen are actually small, immature follicles rather than true cysts in the traditional sense.
Hormonal blood tests. This is often where PCOD and PCOS diverge most clearly. Tests typically include:
✅ LH (luteinizing hormone) and FSH (follicle-stimulating hormone) levels, and particularly their ratio to one another
✅ Testosterone and other androgen levels, which tend to be more significantly elevated in PCOS
✅ Fasting insulin and glucose levels, to check for insulin resistance, which is more characteristic of PCOS
✅ Thyroid function tests, since thyroid disorders can produce similar menstrual irregularities and need to be ruled out
✅ Prolactin levels, another hormone that can affect menstrual regularity when elevated
Metabolic screening. Given the association between PCOS and long-term metabolic risk, many doctors will also check lipid profiles and blood pressure as part of a complete evaluation, especially if there are other risk factors present like a family history of diabetes or cardiovascular disease.
The combination of these findings, not any single result in isolation, is what allows a doctor to determine whether a woman’s presentation fits more closely with PCOD, PCOS, or something else entirely, such as thyroid dysfunction or a different hormonal condition that mimics some of these symptoms.
Why Getting the Right Label Matters
It might seem like a technicality, but the distinction has real consequences for how a woman’s health is managed going forward.
If a woman is told she has PCOS when her presentation is actually closer to PCOD, she may be started on medication she doesn’t necessarily need long-term, or she may be given a more alarming long-term risk picture than is warranted. Conversely, if a woman with true PCOS is told she simply has “PCOD” and needs to lose some weight, she may not receive the metabolic screening and monitoring that her condition actually requires, potentially missing early signs of insulin resistance or cardiovascular risk that could be addressed proactively.
Getting the diagnosis right also shapes the fertility conversation. Since PCOS is more strongly linked to anovulation (the absence of ovulation), women trying to conceive with PCOS may need more structured fertility support, such as ovulation-inducing medication, earlier in their journey than a woman with milder PCOD-related irregularity.
Treatment Approaches: How Management Differs
For PCOD, treatment tends to center heavily on lifestyle modification as the first line of approach:
✅ Structured weight management through diet and regular physical activity, even modest weight loss of five to ten percent of body weight can restore more regular cycles
✅ Reducing refined sugar and processed food intake, which can help stabilize hormonal fluctuations
✅ Managing stress through consistent sleep patterns and stress-reduction practices
✅ Periodic monitoring rather than aggressive medical intervention, unless symptoms are significantly impacting quality of life
For PCOS, management is usually more layered and long-term:
✅ Lifestyle changes remain foundational, but are often paired with medication rather than relied upon alone
✅ Metformin or similar insulin-sensitizing medication may be prescribed to address underlying insulin resistance
✅ Hormonal birth control is frequently used to regulate cycles and reduce androgen-related symptoms like acne and excess hair growth
✅ Anti-androgen medications may be added specifically to manage hair growth and hair thinning symptoms
✅ For women trying to conceive, ovulation-inducing medications or assisted reproductive techniques may become necessary if lifestyle changes and first-line medication don’t restore regular ovulation
✅ Regular monitoring of blood sugar, lipid profile, and blood pressure becomes part of long-term care, given the elevated metabolic risk
The Lifestyle Factor That Applies to Both
Regardless of which condition a woman is ultimately diagnosed with, certain lifestyle principles tend to help both:
✅ Consistent, moderate physical activity, most guidance points toward at least 150 minutes of moderate exercise weekly
✅ A diet built around whole foods, adequate protein, fiber, and healthy fats, while limiting refined carbohydrates and sugary foods that spike blood sugar
✅ Prioritizing sleep quality and duration, since poor sleep is closely tied to hormonal and metabolic disruption
✅ Managing chronic stress, since elevated cortisol levels can worsen both insulin resistance and hormonal imbalance
✅ Avoiding crash diets or extreme calorie restriction, which can actually worsen hormonal irregularity rather than help it
Common Myths Worth Addressing
There’s a fair amount of misinformation surrounding both conditions that’s worth directly addressing:
Myth: You can’t get pregnant with PCOS. This isn’t accurate. Many women with PCOS conceive, sometimes without any intervention, and many others conceive successfully with appropriate medical support. PCOS makes conception more challenging in many cases, not impossible.
Myth: PCOD and PCOS always require lifelong medication. For PCOD in particular, many women see substantial and lasting improvement through lifestyle change alone, without needing ongoing medication.
Myth: If your ultrasound doesn’t show cysts, you can’t have PCOS. Ultrasound findings are only one part of the diagnostic picture. Some women with clear hormonal and metabolic signs of PCOS have relatively normal-looking ovaries on ultrasound, and the diagnosis still stands based on the broader clinical and hormonal picture.
Myth: Weight gain always causes PCOS. The relationship is more complicated and often runs in both directions. Hormonal imbalance from PCOS itself can make weight gain more likely and weight loss more difficult, rather than weight gain being simply a lifestyle failure that causes the condition.
When to Seek an Evaluation
Certain patterns are worth bringing to a gynecologist’s attention rather than waiting them out:
✅ Periods that are consistently irregular, unusually infrequent, or absent for several months at a time
✅ Sudden or progressive weight gain that doesn’t correspond to changes in diet or activity
✅ New or worsening acne, especially along the jawline, or new hair growth in a male-pattern distribution
✅ Hair thinning or hair loss from the scalp that seems disproportionate to normal shedding
✅ Difficulty conceiving after a reasonable period of trying, particularly if cycles are also irregular
✅ A family history of PCOS, type 2 diabetes, or metabolic syndrome, which raises personal risk and may warrant earlier screening
A single symptom in isolation rarely confirms anything on its own. It’s the combination and persistence of these signs, evaluated properly through examination, ultrasound, and bloodwork, that leads to an accurate diagnosis and, from there, a treatment plan that actually fits the condition rather than a generic one size fits all approach.
PCOD and PCOS sit on a spectrum of ovarian and hormonal irregularity, but they are meaningfully different in severity, underlying cause, and long-term health implications. PCOD tends to be the more common, generally milder condition that responds well to lifestyle intervention. PCOS is a more complex metabolic and hormonal syndrome that usually requires more structured, longer-term management, and carries higher risks if left unaddressed.
If you’re experiencing irregular periods, unexplained weight changes, new acne or hair growth patterns, or fertility concerns, the most useful next step isn’t trying to self-diagnose based on symptoms alone, it’s getting a proper clinical evaluation that includes an ultrasound and the right hormonal bloodwork. That evaluation is what actually clarifies which condition you’re dealing with, and more importantly, what treatment approach genuinely fits your situation. Kamla Hospital’s Gynecology department offers this evaluation on Main Pataudi Road, Sector 37D, Gurugram.